Prescribe hormones into a metabolically compromised patient and you are not replacing a deficiency – you are adding a signal to a system that cannot receive it. This is the clinical mistake that explains why so many patients on hormone replacement therapy report partial improvement, no improvement, or new symptoms they did not have before. The metabolic environment has to be ready. Dr. Datis Kharrazian’s clinical training at the Kharrazian Institute addresses metabolic priming before hormone replacement as a prerequisite to outcomes, not an afterthought. What follows is the sequence of thought that separates practitioners who get consistent HRT results from those who keep adjusting doses without resolution.
Why Mitochondrial Function Determines Hormone Replacement Outcomes
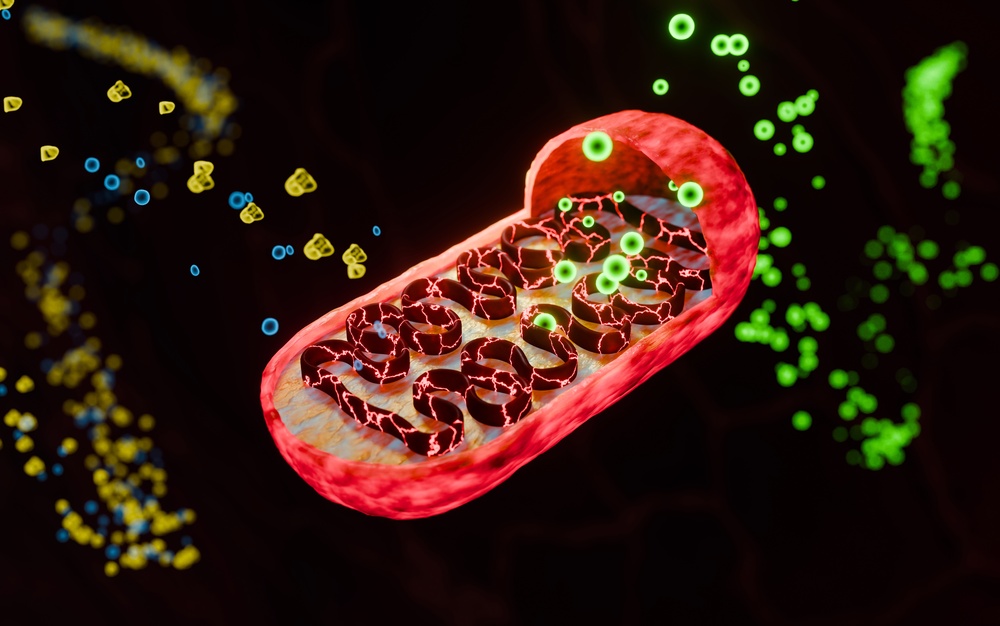
Hormones do not operate independently of cellular energy. Testosterone, estrogen, thyroid hormone, and their downstream effects all require mitochondrial competence. Cells need adequate ATP to translate hormonal signals into biological action. When mitochondrial function is compromised, hormone receptors downregulate, cellular uptake diminishes, and the patient continues to feel the symptoms of deficiency despite measurable serum levels of the hormone being replaced.
Research in neuroendocrinology and cellular metabolism demonstrates that estrogen directly supports mitochondrial biogenesis and protects against oxidative damage within mitochondrial membranes. Testosterone plays a parallel role in maintaining mitochondrial membrane potential and promoting oxidative phosphorylation efficiency. Thyroid hormone regulates the transcription of mitochondrial proteins. These are not secondary effects. They are primary mechanisms. Deficiencies in any of these hormones will degrade mitochondrial output, and mitochondrial dysfunction will in turn blunt the patient’s response to replacement.
The practical implication: before initiating hormone replacement, establish a biochemical baseline for mitochondrial function. Clinically relevant markers include lactate, pyruvate, the lactate-to-pyruvate ratio, carnitine, ammonia, and tissue damage indicators such as CK, AST, and ALT. Elevated ammonia alongside fatigue suggests impaired urea cycle function with mitochondrial involvement. Elevated lactate with a disproportionate pyruvate ratio points to compromised oxidative phosphorylation. These markers tell you whether the engine can run on the fuel you are about to provide.
Insulin Resistance Is a Hormone Replacement Contraindication That Gets Ignored
Insulin resistance may be the most underaddressed contraindication to hormone replacement therapy in functional medicine practice. A patient with unresolved insulin resistance has chronically elevated intracellular glucose, impaired mitochondrial ATP production, and systemic inflammation driven by advanced glycation end products and oxidative stress. Introducing hormone replacement into this environment does not correct the hormonal deficiency – it accelerates the metabolic dysfunction already present.
In women, insulin resistance promotes androgen excess through ovarian stimulation while simultaneously reducing sex hormone-binding globulin, which raises free estrogen and free testosterone disproportionately. The interplay between insulin signaling and gonadal hormone pathways is bidirectional and nonlinear. Attempting to optimize estrogen or progesterone in a patient whose fasting glucose sits at 98 mg/dL and whose triglyceride-to-HDL ratio is above 3.5 is working against the physiology.
The clinical assessment for insulin resistance does not require a glucose tolerance test in most cases. Fasting glucose, fasting insulin, HbA1c, and the triglyceride-to-HDL ratio together provide a reliable picture. Dr. Kharrazian’s clinical training emphasizes that resolving insulin resistance before initiating hormone replacement is not optional when these markers are present. It is the precondition for the therapy to work.
What Nutritional Deficiencies Do to Hormonal Signaling
Hormone synthesis and metabolism are enzymatically driven. Every step in the steroidogenic pathway requires cofactors, and most of those cofactors are nutrients that functional medicine patients are commonly deficient in by the time they present for evaluation.
CoQ10 is essential for mitochondrial electron transport chain function. Without adequate CoQ10, the mitochondria cannot sustain the ATP production that hormonal signaling depends on. B vitamins – particularly B2, B3, and B5 – are direct cofactors in the Krebs cycle and in the enzymatic conversion of steroid hormone precursors. Magnesium is required for over 300 enzymatic reactions, including those governing cortisol production and thyroid hormone conversion. Zinc is a critical cofactor for testosterone synthesis and for the conversion of T4 to the active T3 form of thyroid hormone.
Glutathione deserves specific attention. Oxidative stress impairs hormone receptor sensitivity, degrades steroidogenic enzyme activity, and accelerates hormone catabolism. Glutathione is the primary intracellular antioxidant protecting these processes. Research in oxidative biology consistently demonstrates that depleted glutathione status correlates with reduced hormonal efficacy. Assessing glutathione status, and supporting it before replacement begins, is a foundational step that is frequently skipped because it does not appear on a standard HRT workup.
How Lifestyle Factors Create or Destroy the Conditions for Hormonal Response
Sedentary patients have fewer mitochondria. This is not metaphorical. Research in exercise physiology shows that physical inactivity reduces mitochondrial density through downregulation of PGC-1α, the primary transcriptional regulator of mitochondrial biogenesis. A patient with low mitochondrial density will not respond to hormone replacement the way a metabolically active patient will, because the organelles needed to translate hormonal signals into energy output are simply not there in sufficient numbers.
Exercise is the most potent stimulus for mitochondrial biogenesis available without a prescription. Resistance training and moderate aerobic activity together produce complementary effects: resistance training increases mitochondrial volume within existing muscle fibers, while aerobic conditioning stimulates the production of new mitochondria. Before beginning hormone replacement, patients with significant deconditioning benefit from a structured movement protocol not because movement replaces hormone therapy, but because it creates the cellular infrastructure that makes hormone replacement effective.
Sleep and circadian rhythm disruption are less discussed but equally consequential. Cortisol, growth hormone, and sex hormones are secreted in patterns governed by circadian timing. A patient who sleeps poorly, works night shifts, or has severely disrupted sleep architecture is already running a dysregulated hormonal secretion pattern. Layering exogenous hormone replacement over disrupted circadian timing compounds rather than corrects the problem. Practitioners should address sleep hygiene and circadian entrainment as part of metabolic priming, not as an aside.
The Hormonal Interplay That Changes the Clinical Sequence
Hormones do not exist in separate compartments. The clinical approach of identifying one low hormone and replacing it in isolation ignores the regulatory network those hormones collectively compose.
Thyroid hormone is a compelling example. Hypothyroidism reduces mitochondrial oxidative capacity, impairs cholesterol conversion to pregnenolone, and limits the substrate availability for all downstream steroid hormone synthesis. A patient with unresolved hypothyroidism who receives testosterone or estrogen replacement is working with a compromised steroidogenic pathway from the start. Optimizing thyroid function first – including addressing conversion issues between T4 and T3, which require selenium and zinc – creates a more competent hormonal environment for the replacement to operate within.
The adrenal axis adds another layer. Chronic cortisol excess from unresolved physiological stress competes with progesterone at shared receptor sites and accelerates the catabolism of testosterone. Research in neuroendocrinology demonstrates that pregnenolone steal, where substrate is shunted preferentially to cortisol production at the expense of sex hormone synthesis, is a real and clinically significant phenomenon. Practitioners who begin sex hormone replacement without assessing adrenal output are addressing the downstream deficiency while leaving the upstream driver intact.
Dr. Kharrazian’s clinical training teaches practitioners to think about hormonal sequencing – which system to address first, and in what order to build toward hormonal optimization – rather than treating each hormone as an independent variable. The sequence matters as much as the replacement itself.
Building the Monitoring Protocol After Replacement Begins
Metabolic priming does not end at initiation. Once hormone replacement begins in a patient who has been metabolically prepared, the monitoring protocol needs to be rigorous enough to detect both response and regression.
Biochemical reassessment at 6 to 12 weeks post-initiation should include the same mitochondrial markers used at baseline, alongside updated hormone panels that include free and total fractions, SHBG, and relevant metabolites. Symptom tracking must run parallel to lab assessment. A patient whose serum levels normalize but whose fatigue persists is telling you something the labs are not showing – most commonly, receptor sensitivity has not recovered, or a downstream metabolic bottleneck remains unresolved.
Dose adjustments based on labs alone, without integrating symptom response, produce the cycling pattern of constant recalibration that characterizes difficult HRT patients. The lab is one input. The patient’s functional status is another. Both need to move in the same direction before a protocol is considered successful.
Key Takeaways
- Mitochondrial function determines whether cells can respond to hormonal signals. Biochemical markers for mitochondrial health should be established before hormone replacement begins.
- Unresolved insulin resistance disrupts sex hormone metabolism bidirectionally and reduces the efficacy of hormone replacement. It must be addressed as a precondition, not in parallel.
- Nutritional cofactors – including CoQ10, B vitamins, magnesium, zinc, and glutathione – are prerequisites for steroidogenic enzyme activity and hormone receptor sensitivity.
- Physical activity and sleep normalization increase mitochondrial density and circadian hormone secretion, creating the biological infrastructure hormone replacement requires.
- Hormonal systems are interdependent. Thyroid optimization and adrenal assessment should precede or accompany sex hormone replacement to avoid working against upstream drivers.
Frequently Asked Questions
Metabolic priming refers to the process of optimizing a patient’s metabolic environment before initiating hormone replacement. This includes addressing mitochondrial dysfunction, insulin resistance, nutritional deficiencies, and lifestyle factors that would otherwise reduce the patient’s capacity to respond to exogenous hormones.
Insulin resistance disrupts sex hormone-binding globulin levels, alters free hormone fractions, promotes androgen excess in women, and creates the systemic inflammation and mitochondrial dysfunction that reduce hormone receptor sensitivity. Hormone replacement introduced into this environment is less effective and can worsen metabolic dysfunction.
Clinically relevant mitochondrial markers include lactate, pyruvate, the lactate-to-pyruvate ratio, carnitine, and ammonia. Tissue damage markers – CK, AST, and ALT – provide supporting information. These establish a baseline and help predict how well the patient will respond to hormone replacement therapy.
Hypothyroidism impairs the enzymatic conversion of cholesterol to pregnenolone, limiting the substrate available for all steroid hormone synthesis. Optimizing thyroid function, including T4 to T3 conversion, before or alongside sex hormone replacement creates a more functional steroidogenic pathway and improves outcomes.
Physical activity stimulates mitochondrial biogenesis through PGC-1α upregulation, increasing the mitochondrial density needed to translate hormonal signals into cellular energy output. Patients with significant deconditioning benefit from structured movement protocols before initiating HRT to build the infrastructure that makes replacement effective.
About the Author
Dr. Datis Kharrazian, PhD, DHSc, DC, MS, MMSc, FACN is a Harvard Medical School research fellow and researcher at Massachusetts General Hospital in the Department of Neurology, specializing in autoimmunity and neuroimmunology. He is an Associate Clinical Professor at Loma Linda University School of Medicine and the author of Why Do I Still Have Thyroid Symptoms When My Lab Tests Are Normal and Why Isn’t My Brain Working. Dr. Kharrazian is a Fellow of the American College of Nutrition, a Diplomate of the Board of Nutrition Specialists, a member of the American Association of Immunologists, and a Fellow of the Royal Society of Medicine (UK). The Kharrazian Institute provides clinical education and training to more than 5,000 physicians and healthcare providers worldwide.
Advance your clinical protocols for hormone replacement. The Kharrazian Institute offers practitioner training in metabolic assessment and hormonal optimization. Visit kharrazianinstitute.com to explore current courses.